



We realized recently that in the year we have been doing this, we have never actually gone through the MAiD eligibility criteria in any meaningful detail. Not just listing them off, but actually talking about them — what they mean, how they work in real-world settings, and what they look like in practice.
Let’s be honest, the way they are written — it’s not exactly easy reading. There is a lot of legal and medical language that can make your head spin! So the goal here is to strip all that back and just explain it in simple, tangible language.
We will be following the federal eligibility criteria1, because those apply across the entire country. That said, there are a few small differences in some provinces, so double-check your local MAiD sites for details. And as always, if you have questions, you can send us an email — we really do read them.
We will begin with what is often considered the non-medical criteria, then move into the medical criteria (that’s the big one — the “grievous and irremediable medical condition” part), and then finish with the safeguards, which are the legal checks and balances that are woven through the entire process.
Non-Medical Criteria
Let’s start with the basics.
The person must be eligible for health services funded by a province or territory, or the federal government
This one’s pretty straightforward — they have to be covered under a provincial, territorial, or federal health plan.
So that could be MSP in British Columbia, OHIP in Ontario, or another version in your province or territory. It could also be one of the federal programs — some examples include people in federal prisons, active members of the Armed Forces, or refugee claimants.
The reason for this one isn’t about who deserves MAiD or who doesn’t — it’s about medical tourism. Canada doesn’t want to become a destination where people fly in from other countries to have an assisted death. This rule essentially means you need to be living in Canada and a registered member of the system that funds our health care.
A common misunderstanding is that MAiD is only for citizens or permanent residents — which is not true. Refugee claimants, for example, are typically covered under federal insurance as soon as their claim is accepted.
For new permanent residents, there’s usually a 90‑day waiting period before their provincial health coverage kicks in2; during that time they wouldn’t be eligible for MAiD. That’s the first example of where MAiD has stricter rules than regular medical care. If someone shows up at the ER without public health coverage, they’ll still be treated. But for MAiD, no coverage means no go — it would actually be illegal to proceed.
They must be at least 18 years old and mentally competent
This is one that sounds obvious, but when you start pulling at the threads, it gets interesting.
The law says the person has to be at least 18 years old and mentally competent. Of course, this seems to be a completely arbitrary line — there is no magical shift in maturity or understanding that happens the morning you wake up on your 18th birthday. There are 16 and 17‑year‑olds (and even younger) who have the capacity to understand complex medical decisions better than some adults.
A lot of people — ourselves included — see the current age requirement as more of a placeholder. A line had to be drawn somewhere, but it’s likely that line will eventually need to be revisited. For many experts, the real issue isn’t age — it’s capacity. Some 15-year-olds may have the maturity and understanding needed to make these decisions3 while others may not.
It is also worth remembering that people under the age of 18, often referred to as mature minors, already make major medical decisions. They can refuse blood transfusions, surgeries, or withdraw from life-sustaining treatment—all decisions that could or will inevitably lead to their natural death depending on their medical condition. So it’s not that they are incapable of making choices like these; it’s that the law hasn’t yet caught up when it comes to Medical Assistance in Dying.
Back to the capacity part — because this is key. “Mentally competent” doesn’t mean “perfectly healthy mind.” It means the person has decision‑making capacity for this specific decision, at this precise moment in time, under distinct circumstances. Each medical choice is independent, and the capacity to make each of these decisions is determined...well...independently.4
Can this person make this medical decision, at this time, under these circumstances? That’s really the heart of it. But there’s more to capacity than just answering that question — it has several components and can be assessed in different ways. One common approach looks at whether the person can understand, appreciate, reason, and communicate their decision.
Here’s what that means:
Understand - Does the person understand the important information about their illness and the treatment options available to them?
Appreciate - Do they appreciate how that information applies to them personally? For example, can they apply that knowledge to their particular situation, including what it would mean for them to accept or refuse a treatment?
Reason - Can they demonstrate a reasoning process when considering the options available to them? This is not just having the ability to reason, but to actually demonstrate a reasoning process.
Communicate - Can they communicate a clear and consistent choice?
If they can do all four, they have capacity. And that’s true for saying yes to MAiD, no to treatment, or yes or no to any other medical interventions.
The request must be voluntary
This one’s pretty simple in theory but a little nuanced in practice.
The person has to make the request of their own free will, without undue pressure or influence from external sources. That doesn’t mean they can’t talk it over with their loved ones or their doctor — of course they can. We all make significant life decisions in conversation with other people. It also doesn’t mean a doctor, nurse practitioner, or other health care professional can’t bring MAiD up, if it is appropriate to do so. It just means that the final decision has to be theirs, and theirs alone.
Here’s a funny little quirk of the system: when someone downloads and fills out a MAiD request form — which is publicly available online in most provinces — no one checks right then whether it’s truly voluntary. That part actually comes later, during the medical assessments.
So yes, a person could sit at their kitchen table, fill out the form, mail it in, and that’s it: they’ve made a formal request for MAiD. But voluntariness is examined in detail later by the assessors, who’ll talk with them about their motivations, their understanding of the process, and whether there is any sign of external pressure.
They have to give informed consent to receive MAiD
We’ve talked about this one before, but just to hit the high points: they have to give informed consent — meaning they understand what is happening, what their alternatives are, and what the outcome will be (see "‘Understand, Appreciate, Reason, and Communicate, above).
They cannot delegate it to someone else, like a substitute decision maker, and they cannot write it into a general advance directive (though Quebec has started to allow advance requests for illnesses like dementia).
Consent isn’t just something they give once and never revisit. It’s an ongoing conversation that is assessed continually through the entire process. Finally, they must confirm consent to MAiD immediately before their provision, unless they’ve signed a waiver of final consent (we’ll get to that later).
The Medical Criteria — “Grievous and Irremediable Medical Condition”
This is the big one. It’s the part people tend to think of when they ask, “Do I qualify for MAiD?”
The law says a person must have a grievous and irremediable medical condition. Those are legal words, not medical ones — and they sound more intimidating than they actually are. “Grievous” just means serious. “Irremediable” means incurable, as in there are no medical interventions that can be expected to provide enduring improvement or restore acceptable levels of function.
As this is legal language, it needs to be interpreted through a medical lens, and in the context of a real human being. That is what the MAiD assessors are doing. Grievous and irremediable are quite vague, but luckily the law breaks what this means into three less vague parts.
As we go through these, it can be helpful to think of them in these terms:
The illness, disease, or disability is the cause.
The advanced decline is the loss that comes from the illness, disease or disability.
And the suffering is how the person experiences that loss.
1. They must have a serious and incurable illness, disease, or disability
This criterion is largely determined by the MAiD assessor, who decides whether the person’s condition meets both the medical and legal meanings of these terms.
While it must be a medically recognized illness, disease, or disability, there is no list of what illnesses, diseases, or disabilities are included — and that is actually a good thing. Any list would quickly become outdated and could exclude people who clearly meet the spirit of the law. Instead, it is up to the medical judgment of doctors and nurse practitioners to decide whether the condition in front of them meets the threshold, taking into account the entire picture — the person’s medical situation, their goals, and their values.
Things to note:
“Serious” typically means the condition is significant, enduring, and life-altering — one that profoundly affects the person’s function or quality of life.
“Incurable” doesn’t always mean “impossible to cure.” Sometimes it means “not curable for this person.” In medicine, that nuance matters a lot. A treatment might exist in theory, but if it imposes a significant level of suffering, risk, or burden that outweighs its potential benefit, then it may no longer be considered a realistic or acceptable treatment for that individual. It’s about finding a balance between what medicine can realistically offer and what the person themselves considers tolerable or meaningful.
For instance, if someone with cancer refuses chemotherapy and it is a reasonable and informed refusal — then for them, that illness could be considered incurable. In that sense, incurability is partly a medical fact and partly a reflection of the person’s own determined limitations and choices.
And as if to make it perfectly clear that “serious and incurable illness, disease, or disability” are legal and not medical terms, the law does not consider a mental illness to be an illness, disease or disability for the purposes of MAiD eligibility. In every other context, a mental illness is considered to be an illness, obviously. The exclusion of those with a mental illness is set to change on March 17, 2027.5
2. Must be in an advanced state of decline that cannot be reversed
While we often think of this as physical decline, it can be cognitive in nature as well. Since physical decline is usually better understood, we’ll use an example of cognitive decline below. But first, here is how Jocelyn Downie and Jennifer Chandler define advanced state of decline:
“declines in cognitive as well as physical functions; sudden as well as gradual losses of capability; and ongoing as well as stabilized declines in capability. It is assessed by the medical or nurse practitioner, and it is assessed relative to the patient’s prior capability”.6
For example, someone newly diagnosed with dementia likely wouldn’t be in an “advanced state of decline” just yet. Their illness is serious and incurable, yes, but they may still be functioning independently, recognizing loved ones, and managing most of their own care. In contrast, someone who has progressed to the point where disorientation and loss of self-care abilities have become prominent could be considered in an advanced state of decline.
It is not determined by a particular test or measurement, but by a demonstrable and irreversible decline in function relative to the person’s prior capabilities.
3. Must be experiencing unbearable physical or mental suffering from the illness, disease, disability or state of decline that cannot be relieved under conditions the person finds acceptable
Okay, this one will take a bit longer to explain because this is where it gets personal. Suffering cannot be quantified through any test; it is understood only through the individual’s experience, narrative, and sense of what makes their life meaningful. It pertains to what they have lost, what they can no longer do, or what they know is inevitably coming and find unbearable to face.
Suffering can take many shapes: it can be physical — pain, weakness, shortness of breath, intractable nausea, to name just a few. It can also be psychological or emotional. This includes the loss of dignity, identity, hope, and meaningful connection to others. It can also be anticipatory suffering.
We’ll start with physical and psychological suffering. But instead of trying to describe the differences to you, let’s use the statistics to see how people who have chosen MAiD describe their suffering.
Physical and Psychological Suffering
When we are teaching and ask the audience “what is the most likely cause of suffering for those requesting MAiD?”, almost everyone says “pain.” But according to the statistics this is actually not the main reason people ask for MAiD.
The top four sources of suffering are:7
Loss of ability to engage in meaningful activities — the things that make life worth living for the person.
Loss of ability to perform activities of daily living — feeding, bathing, toileting8
Loss of dignity.
Pain or fear of uncontrolled pain.9
For some people, it might be the pain itself that makes life unbearable. But for many others, it might be what the pain steals from them. Maybe the pain keeps them from walking in their garden, cooking a meal, or playing with their grandchildren. Perhaps it means they cannot get out of bed without assistance, or that they are too drowsy from required pain medication to meaningfully engage in conversation. It’s about the way pain seeps into every part of life, stripping control and the sense of being who they are.
That’s why when people talk about their suffering, they are usually describing the slow erosion of their world — losing the ability to do the small things that make life worth living. For some, it’s not being able to garden or walk the dog; for others, it’s the loss of independence or control, needing help with every basic task, or no longer being recognized by the people they love. These are deeply personal, human experiences of loss, and they’re what make suffering feel unbearable for so many. Physical symptoms can often be eased, at least to some degree, but it’s the losses — the narrowing of one’s world, the erosion of identity, the way illness robs them of what gives life meaning — that tend to carry the greatest weight.
Anticipatory Suffering
“Anticipatory suffering is a form of psychological suffering that is clearly expressed by the person and appreciated by the clinician that relates to a potential future loss or risk caused by a salient aspect of a person’s current medical condition, disease, or disability that otherwise qualifies them for MAiD. A person experiencing anticipatory suffering may meet the eligibility criterion of intolerable suffering right then.”10
There is a difference between anticipating suffering and anticipatory suffering that is important to understand.
Anticipating suffering:
“When I can’t get out of bed, that will be intolerable to me”. This is suffering that one may experience in the future.
Anticipatory suffering:
“My parents suffered horribly through dementia. Now that my own dementia is progressing, I am experiencing significant anxiety and fear about what I know is coming for me”. This is current suffering about a highly possible future state.
A person cannot meet the suffering criterion by anticipating suffering, but might meet the criterion if currently experiencing anticipatory suffering. The difference is subtle, but important.
The Source of the Suffering
The suffering has to come from the illness, disease, disability, or state of decline itself — not from outside circumstances like poverty, housing insecurity, or lack of social supports. Those things can absolutely make life harder, but they are not what this part of the law pertains to. Assessors can spend a lot of time teasing this out — is the suffering really because of the illness, or because of something that could be improved with better social supports, physical supports, etc.? The distinction matters.
Conditions the Person Finds Acceptable
Now, that phrase “cannot be relieved under conditions the person finds acceptable” — this is one of the most misunderstood lines in the entire law. It means the person has to be informed about all the reasonable ways to try to relieve their suffering and has to seriously consider them. They might have already tried some interventions and found them unhelpful. They might reasonably refuse others because, for them, the burden, such as side effects or invasiveness, outweigh the benefits. Think about individuals living with metastatic cancer who have already gone through multiple rounds of chemo and all its side effects. If they state, “I cannot go through chemo again” that will likely be considered a reasonable refusal.
Just like someone needs capacity to say yes to treatment, they also need capacity to say no. And the more serious the consequences, the higher that bar becomes. With MAiD, where the outcome is death, that threshold is understandably high. The person needs to show they fully understand what they are refusing, appreciate what that means for them, can reason through it, and communicate a consistent decision. Sound familiar?
Benefit-to-Burden Balance
Sometimes assessors will hit pause on the MAiD process if there is a treatment or support that seems like it could realistically help the individual.
If an assessor believes there is an intervention with a very positive benefit-to-burden balance — something that has a good chance of helping and would place very little burden on the person, like a minor procedure or simple adaptive aid — they might say, “Let’s try this first.” The person can always decline, of course, and no treatment will ever be forced on anyone.
However, if the assessor feels that the option offers a high likelihood of benefit with minimal burden, and the person chooses not to try it, the assessor might not feel comfortable concluding that all reasonable options have been seriously considered. In that case, they may decide they cannot move forward with the MAiD process until that question is addressed.
On the other hand, if the person does try the intervention and it does not provide the hoped-for benefit, then the requirement to seriously consider reasonable alternatives has likely been met — at least for that intervention — and the assessment process can move ahead from there.
Reasonably Foreseeable Death or Not
Reasonably foreseeable natural death is often referred to as “Track 1”
No reasonably foreseeable natural death is often referred to as “Track 2”
What Does “Reasonably Foreseeable Natural Death” Mean?
This is one of the more confusing parts of Canada’s MAiD legislation partly because there is no medical definition of what a reasonably foreseeable natural death actually is. These are legal terms that must be interpreted by medical professionals, based on the totality of a person’s circumstances.
In general, having a reasonably foreseeable natural death means that a person’s death is reasonably predictable because their medical condition makes the trajectory toward death clear and foreseeable. Unlike other countries, the law does not require a formal prognostic timeframe (i.e. prognosis of 6 months) and the person does not need to be “terminally ill” or expected to die within short weeks or months.
Assessors look at the entire clinical picture: how advanced the person’s illness, disease or disability is, how fragile or medically complex they are, and whether the course of their condition makes their death predictable in the reasonably foreseeable future.
People whose natural death is not reasonably foreseeable are still eligible to request MAiD — but the law adds additional safeguards, which we’ll discuss next.
Safeguards
In addition to meeting all the eligibility criteria discussed above, anyone found eligible for an assisted death must also meet certain safeguards. These are built into the law to ensure that every MAiD request is voluntary, well-considered, and thoroughly assessed.
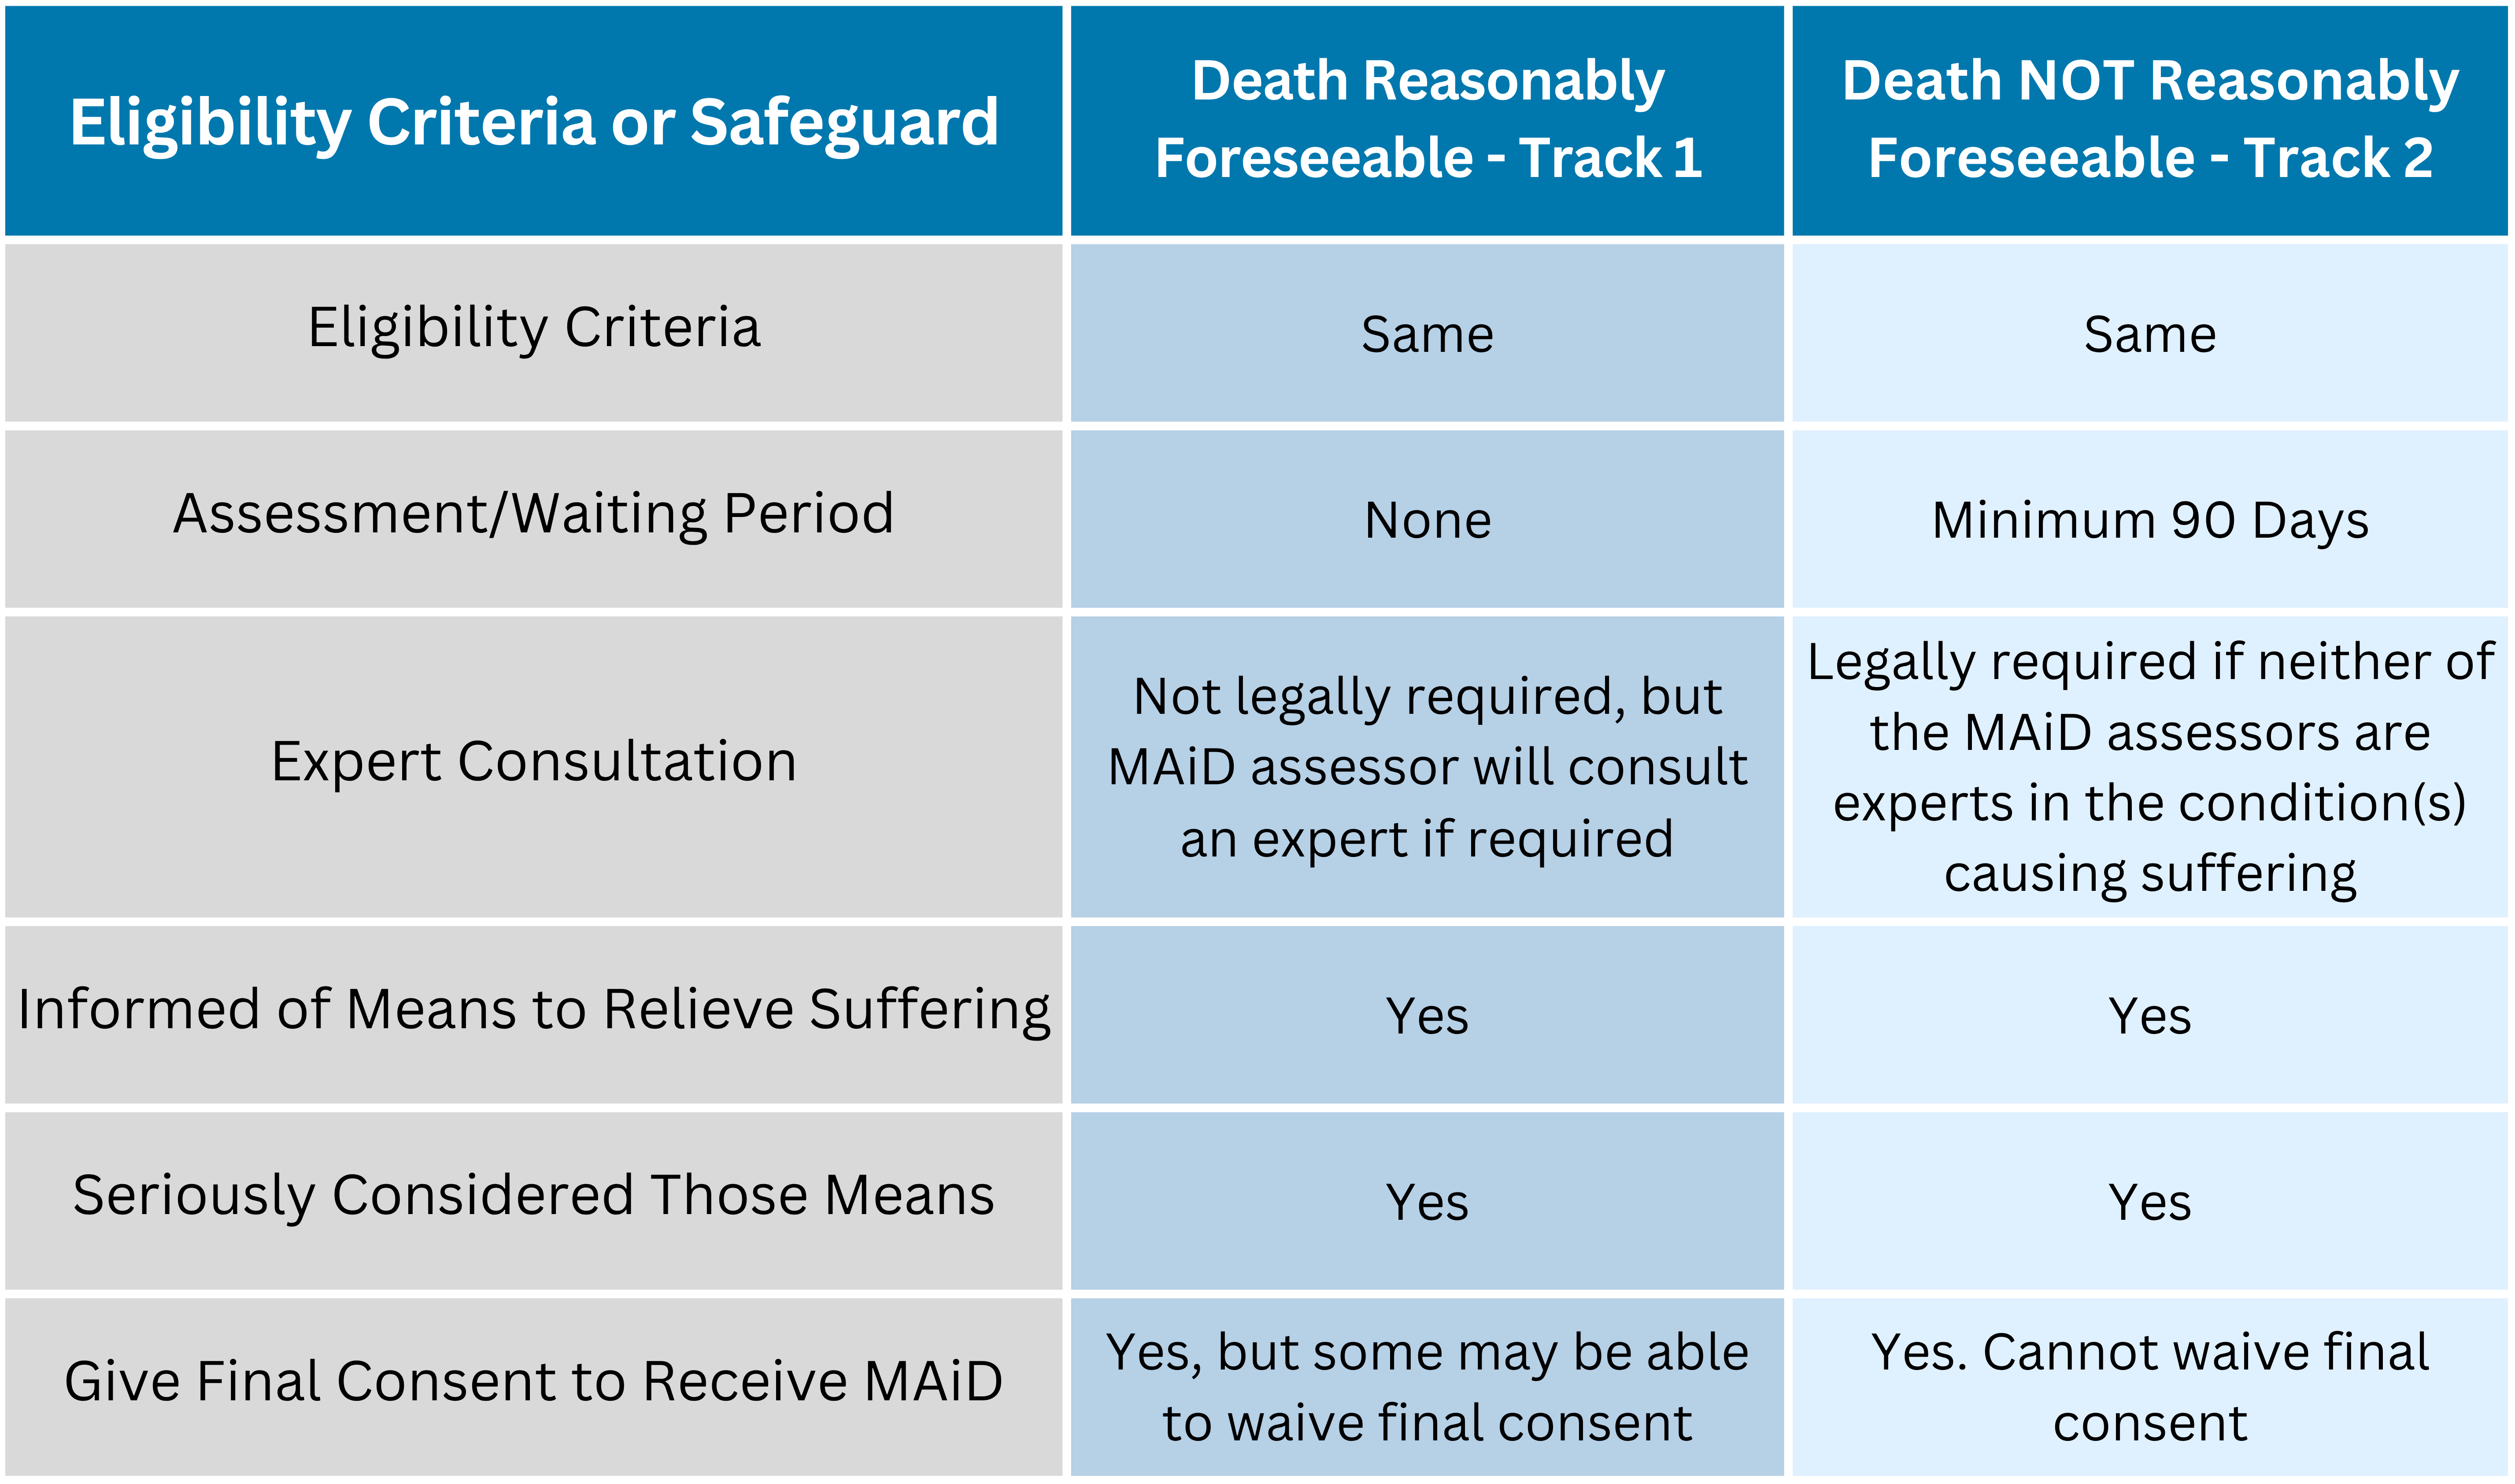
Some of these safeguards are common to both tracks — that is, they apply whether a person’s natural death is reasonably foreseeable (Track 1) or not (Track 2). Others apply only to people whose natural death is not reasonably foreseeable, adding an extra layer of protection and reflection in those cases.
Let’s start with the safeguards that apply to both Track 1 and Track 2.
Safeguards that apply to everyone (Track 1 and Track 2)
Consent is required. Only the person themselves can consent — not a substitute decision‑maker, a family member, or through an advance directive.
Written request with a witness. The request has to be in writing, signed and dated by the person (yes, with a pen — not digital), and witnessed by one independent person. That witness cannot be someone who benefits from the person’s death, which almost always excludes family.11
Right to withdraw. The person must know they can withdraw their request at any time, for any reason, right up until the last moment.
Two independent assessments. Two practitioners have to agree that the criteria are met. Here, “independent” does not mean they cannot speak to each other — it just means there is no reporting relationship or other conflict of interest that might impact their ability to make an independent eligibility assessment.
Final consent at the time of provision. Before medications are given, the person has to have capacity and confirm their consent to receive the medications that will end their life — unless they’ve signed a waiver of final consent (which is only available under Track 1). More on the waiver of final consent below.
Extra safeguards for Track 2 (when death is not reasonably foreseeable)
Here’s what gets added on top:
At least one assessor must have expertise in the condition causing suffering. If neither does, they must legally consult an expert — someone who can confirm the diagnosis, prognosis, and outline possible treatments or supports. (That expert doesn’t decide eligibility; they just make sure the assessors have all the relevant facts.) For example, the expert could be an oncologist, a psychiatrist, or a physiatrist — yes, we read those last two incorrectly as well sometimes — or it could be a physical or occupational therapist. The important thing to remember is that the assessor is required to consult with a clinician who has the relevant expertise to help them fully understand the person’s condition, its typical progression, and the range of available treatment or support options.
The person must be informed about all reasonable means to relieve suffering. This includes being provided with access to palliative care services, psychological or spiritual counselling, community or disability supports, and other interventions that might improve quality of life or relieve suffering. The goal is not to compel the person to pursue these options, but to ensure that their decision is made with a full awareness of what supports are available.
Everyone has to agree that the person has seriously considered those options. That doesn’t mean they have to try everything. It just means they have looked at the possibilities and made a reasoned decision about what is acceptable to them.
There is a minimum 90‑day assessment period.
It has to take at least 90 days from the start of the first assessment to their assisted death — unless the person is at imminent risk of losing capacity, or their death becomes reasonably foreseeable (in which case it switches to Track 1). In practice, Track 2 assessments often take longer, depending on how long it takes to explore options. This time isn’t simply a waiting period; it allows assessors and the person requesting MAiD to explore and thoughtfully consider reasonable alternatives, discuss what is and isn’t acceptable, and confirm that any remaining treatments or supports have been offered, attempted, or reasonably declined before proceeding.
Eligibility and Safeguards Overview
The Waiver of Final Consent (Track 1 only)
This one always deserves its own article, but we’ll do a quick overview here.
If someone has been found eligible under Track 1, has picked a date, and is at risk of losing capacity before that date, they might be able to sign a Waiver of Final Consent.
The waiver is a legal agreement between the person approved for MAiD and their MAiD provider — it can’t be transferred to another provider. It’s important to remember that the waiver of final consent might not be appropriate for everyone, even if they meet the criteria listed below. Only the MAiD provider can determine if the waiver is appropriate for an individual’s specific situation.
In order for the waiver to be a potential option, the person must:
Already be found eligible under Track 1.
Still have capacity when signing the waiver.
Have chosen a date for MAiD.
Be at risk of losing capacity before that date.
If they lose capacity on or before the chosen date, that MAiD provider can proceed without final consent. But — and this is extremely important — the waiver gives permission, not an obligation. If providing MAiD is deemed unnecessary (i.e. the person is comatose, comfortable, and in their final hours of life), or if the person shows any sign of refusal (even non‑verbal, like pushing away the IV or shaking their head), the provider will not proceed.
So that’s the overview — the non-medical criteria, the medical ones, and the safeguards.
If you made it this far, we’d love to know what you think. Thank you, as always, for supporting our work! Paul and Kim
In health care, capacity is presumed unless there’s a reason to think otherwise. That’s still true with MAiD — but the law adds an extra layer. Assessors can’t simply assume someone has capacity; they have to confirm it. In practice, they either establish that the person has decision-making capacity, or ensure there is absolutely no reason to believe they don’t.
The next six are, in order: loss of independence; perceived burden; inadequate control of symptoms other than pain; emotional distress, anxiety, fear or existential suffering; loss of control of bodily functions; and isolation or loneliness. It’s important to note that while burden and isolation and loneliness are tracked, these are not reasons a person can have MAiD. We’ve written about this before.
If the person cannot write the request or sign and date it themselves, there is an option for a proxy to sign and date it on their behalf, and at their express direction.
This is an incredible article, though it takes an entire cup of tea to get through it. It may be over the head for those seeking MAiD, but it should be considered essential reading for everyone who counsels others. I will be posting this on our website and our socials. Thank you!
This is the best write-up about understanding MAiD I have read/seen so far! Very well written, thoughtful and easy to understand. Which does NOT make it an easy topic - on the contrary, as the devil is in the details and in the interpretations. But it helped me with a better understanding. I am very interested in this topic and reading & studying all I can to hopefully actively contribute as a volunteer when I am ready. Please keep up the good work and writing!